The Malo Bridge. Individual Crowns on a Titanium Bar.
A precision-milled titanium framework, screwed to your implants, carrying a separate crown for every tooth — so a chipped tooth is a crown replacement, not a new arch. The design Dr. Paulo Maló developed and published, built in Plano.
Also known as: the thimble bridge, thimble bar, or crown-and-bar prosthesis.
What Is a Malo Bridge?
Most full-arch "implant teeth" today are milled from a single solid block of zirconia — one heavy, monolithic piece. The Malo bridge takes the opposite approach: it is built the way nature builds a smile, one tooth at a time.
The short version: a Malo bridge is a lightweight titanium framework, screwed securely to your implants, with individual crowns cemented onto thimble-shaped copings built into the bar — which is why many people call it a thimble bridge or thimble bar. Each tooth is its own crown. Each crown can be serviced on its own.
An actual Malo bridge, mid-assembly. The individual crowns are cemented one by one onto the thimble-shaped copings of the milled titanium bar — the exposed gold “thimbles” at the end are what give the design its nickname. Note how thin and light the framework is next to a solid zirconia block.
The design carries the name of Dr. Paulo Maló, the Lisbon clinician whose group developed and published the All-on-4 protocol — four implants placed at strategic angles to reach the denser bone at the front of the jaw, which is what lets many patients avoid bone grafting. The bridge he designed to sit on those implants is the one described on this page. How that came about is worth the two minutes, because it explains why the prosthesis is built the way it is.
1
The Titanium Bar
A CAD/CAM precision-milled titanium framework. Titanium is what aircraft and medical implants are made from: exceptionally strong, biocompatible, and a fraction of the weight of a solid ceramic arch. Because it's milled to a passive fit, it seats on your implants without stress or strain.
2
The Thimbles
Built into the bar are thimble-shaped copings — one per tooth. These are the "thimbles" the nickname comes from. Each one is a precise foundation that an individual crown seats onto, just like a crown on a prepared natural tooth.
3
Individual Crowns
Each tooth is a separate crown — with its own shape, translucency, and natural separation from its neighbors — cemented onto its thimble. Chip one? Replace one. The other teeth, the bar, and your implants are untouched.
The finished bridge is screw-retained to your implants: fixed in your mouth like natural teeth, never removable by you, but easily removable by your dentist for maintenance, professional cleaning, or a crown repair. That combination — fixed for you, serviceable for us — is the heart of the design.
Where the Malo Bridge Came From
Most prosthetic designs are named after a lab or a material. This one is named after a
clinician, and the story explains the engineering.
The problem, in the late 1990s
A patient who had lost all their teeth faced a hard choice. The bone at the back of the jaw resorbs
first and fastest, and it sits next to two structures you cannot drill through — the maxillary
sinus above, the inferior alveolar nerve below. Putting implants back there usually meant bone
grafting, sinus lifts, and the better part of a year in a denture waiting for it all to heal. Plenty
of people simply did not do it.
What Dr. Maló’s group did about it
Dr. Paulo Maló is a Portuguese dentist practising in Lisbon. He did not invent
dental implants, and it is worth being straight about that: osseointegration was Per-Ingvar
Brånemark’s, tilting the back implants to avoid the sinus and the nerve had been described by
Krekmanov and by Mattsson at the end of the 1990s, and immediate loading was already being tried.
What Maló’s group did was put those pieces together into one protocol, run it on real patients,
and — the part that actually mattered — publish the results.
The first paper appeared in 2003: 44 patients, 176 implants, four per jaw, the back two tilted to
catch the dense bone at the front, and a fixed provisional bridge fitted within two hours of
surgery. Prosthesis survival was 100%, implant survival 96.7–98.2% at six months.[1]
They called it All-on-Four. The upper jaw, which is harder, followed; by 2012 that group had
three- and five-year outcomes published for completely edentulous maxillae.[2]
The protocol held up. A longitudinal study of 980 implants in 245 patients followed
for up to ten years reported implant success of 94.8% and prosthesis survival of
99.2%.[3] That is the evidence base underneath the four-implant
approach most of the industry now sells.
And then the teeth themselves
Here is the part that gets lost. Having worked out how to anchor a full arch on four implants,
Maló’s group still had to decide what the teeth should be made of — and they did not choose a
single block. They chose a milled titanium framework carrying individual ceramic crowns,
and published ten years of follow-up on it.[4] The reasoning is structural rather
than cosmetic: titanium flexes a little and dissipates the small stresses that a rigid ceramic arch
would pass straight into the screws and the bone, and separating the teeth from the structure means
the part most likely to break is also the part easiest to replace.
That bridge is the one that took his name. The contemporary version is built the same way — a
CAD/CAM titanium bar, multi-unit abutments to correct implant angulation, thimble copings, and
individual zirconia crowns cemented on, with the whole assembly still screw-retained so a dentist
can take it off.[5] Three decades of digital manufacturing have changed how it
is made. They have not changed what it is.
Why any of this matters to you. A monolithic zirconia arch is a genuinely good
restoration and we place them. But it is the later, lab-efficient way to make a full arch, and
when it fractures the whole arch is remade. The Maló design was drawn around the opposite
assumption: that teeth get chipped, worn and knocked over a lifetime, so the teeth should be the
serviceable part. You are not buying a brand name. You are buying a prosthesis someone designed
to be repaired.
Innate Dental Solutions is an
independent practice in Plano, Texas. We are not affiliated with, endorsed by, or a franchise of
MALO CLINIC or Nobel Biocare. All-on-4 is a registered trademark of Nobel Biocare Services AG;
we use it, as the clinical literature does, to name the surgical protocol. “Malo bridge” is
used here as the descriptive name the dental literature gives this prosthetic design.
How Many Implants — and Why It Is Not Always Four
The All-on-4 name has made four sound like a fixed rule. It is not. Four angled implants is the
protocol Dr. Paulo Maló developed and it works well in a great many cases — but the number that
belongs under your arch is a question about your bone, not about a brand name.
We place four to six implants under a Malo Bridge. Where there is good bone volume,
five or six spreads the chewing load over more anchor points and gives you redundancy: if one implant
were ever lost, the bridge still has support while it is dealt with. On four, losing one is a bigger
problem. Heavy bite forces and bruxism push the same way.
More is not automatically better, and we will not sell you implants you have no bone for. Placing six
where there is only room for four means shorter or narrower fixtures in poorer bone, which is a worse
outcome, not a more thorough one. Some arches are genuinely best restored on four. Your CBCT settles it,
and we will show you the scan and explain the reasoning rather than quoting a package.
One consequence worth knowing: strictly speaking, a bridge on five or six implants is
All-on-X rather than All-on-4. You will see both terms used, here and everywhere else.
They describe the same family of treatment — a fixed full arch on a small number of strategically
angled implants.
Left — the Maló bridge: a milled titanium bar with individual crowns seated on its thimble copings, so a single tooth can be replaced without remaking the arch. Right — monolithic zirconia: the whole arch milled from one solid block. The sequence runs bar, crowns going on, the zirconia arch, then the two together.
Representative render of the components, not a photograph of a patient’s case. Which design suits a given arch depends on bite force, available bone and what the CBCT shows.
Most full-arch practices in the Dallas–Fort Worth area deliver a monolithic zirconia bridge as the final restoration. It's a legitimate, strong prosthesis — and we'll be honest below about where it wins. But there are real differences you should understand before choosing, because you will live with this decision every day, for decades.
Malo Bridge Innate's Premium Arch
Monolithic Zirconia Block
Construction
Milled titanium bar + individual crowns cemented on thimble copings
Entire arch milled from a single solid block of zirconia
Weight in your mouth
Light — thin titanium frame carries most of the structure
Heavy — solid ceramic across the whole arch; many patients notice the mass, especially in the upper jaw
Aesthetics
Individual crowns with natural contours, separations, and tooth-by-tooth translucency
Teeth are carved from one block, then stained and glazed; can read as uniform, opaque, and "denture-like" up close
If a tooth chips
Replace that one crown; the rest of the bridge is untouched
Chips can sometimes be polished — but a crack or fracture typically means remaking the entire arch
Fit on your implants
Titanium is slightly ductile and milled to a passive fit — gentle on implants and screws
Zirconia is rigid and brittle; a less-than-passive fit transfers stress to implants and screws
Bite feel & opposing teeth
Crown materials chosen per patient; framework design helps distribute force
Extremely hard surface; polished zirconia is kind to opposing teeth, but the solid mass transmits force directly
Long-term serviceability
Designed to be maintained for decades — crowns are the renewable part
Serviceable only as a whole; major damage restarts the lab process from scratch
Cost over 20 years
Higher up front; small, targeted repairs over time
Often cheaper up front; a single fracture can cost more than the difference
Heritage
The design Dr. Paulo Maló’s group published alongside the All-on-4 protocol, with ten years of follow-up[4]
A one-piece design that came later, as zirconia milling matured
Weight: you wear this every day
A solid zirconia arch is exactly what it sounds like — a dense ceramic block spanning your whole jaw. Zirconia is one of the densest materials used anywhere in dentistry, and in the upper arch especially, patients report feeling the mass. The Malo bridge replaces most of that ceramic bulk with a thin, rigid titanium frame. The result is a prosthesis that feels closer to natural teeth and less like an appliance.
Aesthetics: teeth are individuals
Look closely at a natural smile: every tooth has its own shape, its own translucency at the edge, and a subtle separation from its neighbor. A monolithic bridge is carved from one uniform block and colored on the surface. A Malo bridge is assembled from individual crowns — so light passes through each tooth the way it does through enamel, and the embrasures (the small spaces between teeth) are real, not etched into a slab. It photographs better, and it reads as natural from a conversation away and up close.
Repairability: the difference that shows up in year five
Everything in the mouth eventually needs service — that's not pessimism, it's dentistry. The question is what service looks like. On a Malo bridge, a chipped or worn crown is removed and replaced individually while the bar, the other crowns, and your implants stay exactly where they are. On a monolithic arch, a true fracture generally means the whole prosthesis comes off and a whole new one is made: new records, new lab cycle, new delivery. The Malo bridge turns a major event into a minor appointment.
Engineering: why the titanium bar matters
Titanium frameworks are milled to a passive fit — the bar seats on all implants simultaneously without being flexed into place. Because titanium has slight ductility, small stresses dissipate instead of concentrating. Zirconia has enormous compressive strength but is brittle: it doesn't bend, it breaks, and any misfit stress goes somewhere — into screws, into the ceramic, or into the bone around your implants. This is one reason full-arch frameworks were titanium for decades before zirconia milling made the one-block shortcut economical for labs.
Where monolithic zirconia honestly wins
We publish our pricing, and we'll publish our trade-offs too. As a single piece, monolithic zirconia has no cemented interfaces, so there are no individual crowns that could ever debond — and for severe grinders (bruxers), its one-piece strength is a real argument. If you brux heavily, we'll talk about that openly at your consult: sometimes the answer is a Malo bridge plus a nightguard, sometimes it's managing the muscle activity itself, and occasionally monolithic zirconia is the right call for your case. The point of this page isn't that zirconia is bad — it's that you should get to choose with the full picture, which most patients are never shown.
What the research shows — including the part that is not flattering
This prosthesis has its own published follow-up, from Dr. Maló’s own group. A retrospective study of 125 bridges in 108 patients, all built as a CAD/CAM titanium framework with individual ceramic crowns cemented onto it, followed patients from nine months to ten years. Cumulative prosthesis survival was 92.4% at ten years in the earlier group and 100% at five years in the later one — 96% overall.[4]
The same study is candid about complications, and so are we: the most common one was crown fracture, and it was not rare. That is the honest case for this design rather than against it. On a one-piece arch a fracture means the whole prosthesis is remade. On this one it means the crown that broke is replaced while the bar, the other crowns and your implants stay where they are. The study also found that biting against another ceramic implant bridge roughly doubled the odds of a crown fracture — the kind of detail that should change what we plan for you, and one we will raise at your consultation if it applies.[4]
Already Have an All-on-X? It May Convert to a Malo Bridge.
You don't have to start over to upgrade. If you already have a full-arch implant bridge — an acrylic hybrid that's worn, stained, or bulky, or a zirconia arch that feels heavy, looks flat, or has chipped — a Malo bridge can often be fabricated onto the implants you already have, usually with no new implant surgery.
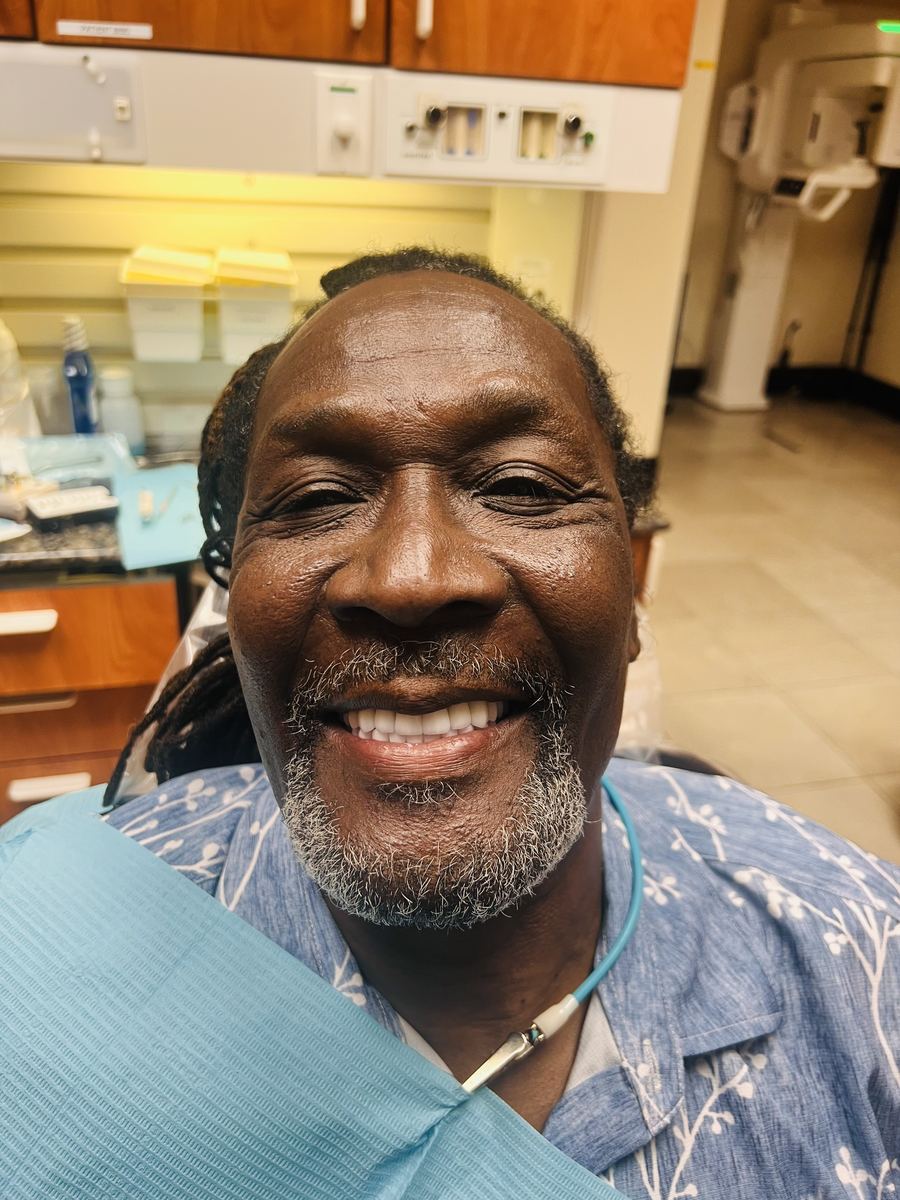
A real Innate full-arch patient at delivery. Individual crowns give the smile natural separations and translucency — see more results on our Before & After page. Photo shared with patient permission.
Why patients convert
Weight and bulk. The single most common complaint we hear about monolithic zirconia arches: "it feels like a brick." A titanium-framed Malo bridge is dramatically lighter.
Aesthetics. Uniform, opaque, "obviously fake" teeth — especially noticeable in photos and up close. Individual crowns restore the translucency and separation of natural teeth.
A fractured or chipped prosthesis. If your zirconia arch has already cracked, you're facing a full remake anyway. That's the moment to remake it into something serviceable, so you never face this decision again.
A worn acrylic hybrid. Acrylic teeth on the original hybrid design wear, stain, and pick up odor over the years. Converting to a Malo bridge is the definitive upgrade path.
Stability and bite. A new, passively fitting milled bar can improve how evenly your bite loads across the implants — protecting screws, prosthesis, and bone.
How a conversion runs, and when it is not advisable.Converting an existing full-arch case sets out the four steps, what makes a case a good candidate, what has to be treated first, what is warranted when we did not place the implants, and what it costs →
Pricing & Warranty — Published, Like Everything We Do
The complete All-on-4 Malo Bridge at Innate Dental Solutions is $17,500 per arch — the price for treatment plans accepted on or before December 31, 2026, rising to $25,000 per arch on January 1, 2027 (terms) — all-inclusive, published pricing, in an area where full-arch cases routinely quote far higher. The bridge carries a lifetime warranty against cracks and chips, and financing is available.
Conversion cases are quoted after your free evaluation, because the right plan depends on your existing implants — but the quote you get is the price you pay, in writing, before anything starts. See how the Malo bridge compares to our other options — single implants from $2,100, snap-on dentures at $8,000, and the fixed full arch at $13,000 — on our Implant Options page.
Malo Bridge FAQs
Is a Malo bridge the same thing as a thimble bridge or thimble bar?
Yes — same design, different names. The "thimbles" are the crown-shaped copings on the titanium bar that each individual crown seats onto. You may also hear it called a crown-and-bar or Malo-style prosthesis. If a dentist has told you that you have (or should get) a thimble bar, this page is describing that restoration.
Is the Malo bridge an All-on-4?
The Malo bridge is the prosthesis — the teeth — and All-on-4 is the implant protocol underneath it: four implants placed at strategic angles so most patients need no bone grafting. In practice we place four to six implants under a Malo Bridge depending on what your bone supports — strictly speaking that makes many of our cases All-on-X rather than All-on-4. Dr. Paulo Maló developed both together. At Innate, "All-on-4 Malo Bridge" means the original pairing: the angled-implant protocol restored with the individual-crown bridge it was designed for.
Which is stronger — Malo bridge or monolithic zirconia?
They're strong in different ways. Zirconia has tremendous one-piece hardness, but it's brittle — when it fails, it fails as a whole. The Malo bridge builds its strength on a titanium framework (the same class of material used in aerospace) and treats the crowns as the renewable surface. For most patients the meaningful question isn't peak strength — both handle normal chewing easily — it's what happens over 10–20 years of real life, where the Malo bridge's tooth-by-tooth serviceability wins.
Can my existing All-on-4 / All-on-6 / All-on-X convert to a Malo bridge?
Often yes, without new surgery, if your existing implants are healthy, stable, well-positioned, and on a restorable platform. It genuinely depends on implant quality — bone loss, infection, failing implants, or poor positioning may require treatment first, and occasionally conversion isn't advisable. A free evaluation with a CBCT scan gives you a definitive answer.
What happens if a crown on my Malo bridge chips?
We remove the bridge, replace that single crown, and re-secure the bridge. The other teeth, the titanium bar, and your implants aren't touched. Compare that to a fractured monolithic arch, which typically must be remade in its entirety — and note that our Malo bridge carries a lifetime warranty against cracks and chips.
I grind my teeth. Can I still get a Malo bridge?
Usually yes, with a plan. Bruxism (grinding) is hard on every prosthesis — and on the implants under it — regardless of material. Depending on severity we may recommend a nightguard, muscle-relaxing treatment, or in heavy cases discuss whether monolithic zirconia's one-piece construction suits you better. We'll give you an honest recommendation for your bite, not a one-size-fits-all answer.
How do I clean a Malo bridge?
Like fixed teeth: brushing, a water flosser, and cleaning under the bridge daily, plus regular professional maintenance visits where we can remove the bridge, clean everything thoroughly, and inspect each component. Because the bridge is dentist-removable by design, hygiene maintenance is more thorough than with a permanently cemented restoration.
How long does the whole process take?
For new full-arch cases, you leave surgery with a fixed provisional — our in-house lab delivers fixed provisionals in as little as 48 hours — and the final Malo bridge is fabricated after your implants have fully integrated, typically a few months later. Conversion cases skip surgery entirely in most instances and move at the pace of records, design, try-in, and delivery.
This page is general
information about a treatment option, not a diagnosis or a treatment recommendation. Individual
outcomes vary and depend on your clinical presentation, your bone and your bite. Survival figures
above are from the published studies cited and are not a prediction about your own case or a
guarantee of any result. Prices shown are current as of October 2026 and apply to Innate Dental
Solutions of Plano.
See and Feel the Difference in Person
Hold a Malo bridge in one hand and a monolithic zirconia arch in the other — the comparison takes about five seconds. Then let's look at your scan and talk through your options with published pricing and honest timelines.